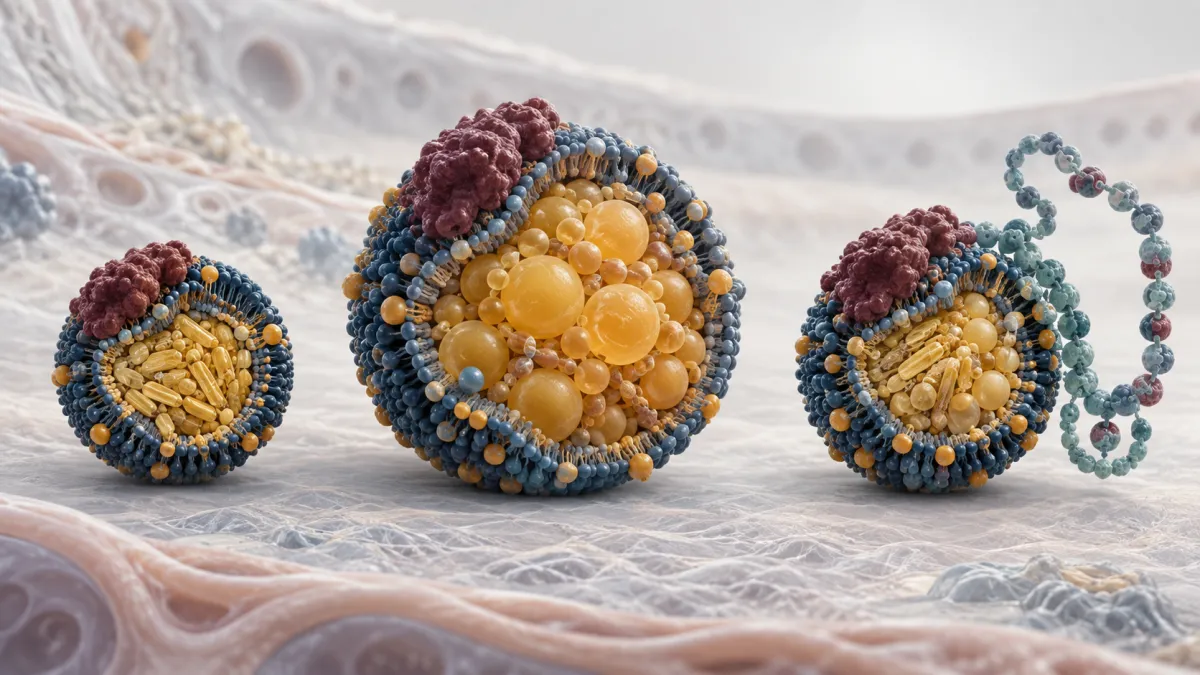
Are All ApoB Particles Equally Dangerous?
Introduction
ApoB has become one of the most useful markers for understanding cardiovascular risk. Unlike LDL cholesterol, which measures the amount of cholesterol being transported, ApoB approximates the number of atherogenic lipoprotein particles circulating in the blood. Each LDL, VLDL, IDL, remnant and Lp(a) particle carries one ApoB molecule, making ApoB a practical count of the particles capable of entering the arterial wall.
That principle remains intact: greater exposure to ApoB-containing particles increases the opportunity for those particles to become retained within arteries and initiate atherosclerosis. However, counting particles may not describe every biological effect those particles produce after entering circulation or interacting with the vessel wall.
A new study published in the European Heart Journal examined whether LDL, triglyceride-rich lipoproteins and Lp(a) are associated with different patterns of circulating proteins. Researchers analyzed 2,918 plasma proteins in 35,269 UK Biobank participants without known cardiovascular disease and replicated the findings in another 5,915 participants from the Multi-Ethnic Study of Atherosclerosis.
The differences were striking. Investigators identified 30 proteins associated with LDL, 471 associated with triglyceride-rich lipoproteins and 53 associated with Lp(a). The triglyceride-rich lipoprotein and Lp(a) signatures overlapped with each other much more than either overlapped with the LDL signature, particularly in pathways connected with immune activation, inflammation and vascular remodeling.
The researchers estimated that these proteomic changes statistically mediated approximately 62% of the coronary risk associated with triglyceride-rich lipoproteins and about 14% of the risk associated with Lp(a). These percentages come from mediation modeling and should not be interpreted as proof that the identified proteins directly caused those exact proportions of cardiovascular events.
The study does not weaken the case for ApoB testing. All three lipoprotein groups contain ApoB, and each is implicated in the development of coronary artery disease. Instead, the findings introduce a second layer of risk: ApoB measures how many atherogenic particles exist, while the type, composition and biological activity of those particles may influence what happens after exposure.
This distinction may be particularly important in insulin resistance, where triglyceride-rich remnants can increase even when LDL cholesterol appears acceptable. It may also help explain why Lp(a) carries risks that are not fully captured by ApoB alone, including oxidized phospholipids and inflammatory effects associated with its unique structure.
The new study therefore supports a more complete question than simply asking whether ApoB is high: Which ApoB-containing particles are elevated, and what biological pathways might they be activating?
In this article, we will examine what ApoB measures, how LDL particles differ from triglyceride-rich remnants and Lp(a), what the proteomic findings actually show, and how ApoB, triglycerides, remnant cholesterol, Lp(a) and inflammatory markers can be interpreted together.
🎧 Listen to the Episode: What ApoB Alone Can't Tell You
ApoB answers one of the most important questions in cardiovascular prevention: how many atherogenic particles are circulating in your blood? But emerging research is pushing the conversation one step further by asking whether different ApoB-containing particles carry the same biological risk.
In this episode of The Health Pulse, we explore LDL, triglyceride-rich remnants, and Lp(a) and examine new proteomic research showing striking differences in the inflammatory and vascular pathways associated with each. We also connect those findings to insulin resistance and explain how a more complete testing strategy can uncover risk that LDL-C alone may miss.
▶️ Click play below to listen, or keep reading to discover why cardiovascular risk may depend not only on how many ApoB particles you have, but also on what kind of particles they are and the metabolic environment they're traveling through.
What ApoB Actually Measures
Apolipoprotein B is a structural protein found on the surface of particles capable of contributing to atherosclerosis. Liver-derived VLDL, IDL, LDL and Lp(a) particles each contain one molecule of ApoB-100. Intestinal chylomicrons and their remnants contain a shorter form called ApoB-48.
Because there is generally one ApoB molecule per atherogenic particle, measuring ApoB provides an estimate of the total number of these particles in circulation. In a fasting sample, the result is dominated by ApoB-100-containing particles because relatively few chylomicrons are normally present.
This differs from LDL-C. LDL cholesterol measures the mass of cholesterol being carried inside LDL particles, not how many particles are carrying it. Two people can have the same LDL-C while one has fewer cholesterol-rich particles and the other has many cholesterol-poor particles.
That discordance frequently appears with insulin resistance. Increased production of triglyceride-rich VLDL can ultimately generate a larger number of smaller LDL particles. LDL-C may remain deceptively acceptable because each particle carries less cholesterol, while ApoB reveals that the total atherogenic particle burden is elevated.
ApoB is therefore valuable because every additional particle represents another opportunity to cross the endothelium, become retained within the arterial wall and participate in plaque formation. This is why particle number adds important information beyond the cholesterol concentration shown on a conventional lipid panel.
However, ApoB does not identify the particles individually. A result of 120 mg/dL does not reveal how much of that burden comes from LDL, VLDL remnants, IDL or Lp(a). It also does not describe the particles’ triglyceride content, cholesterol content, size, oxidation state or associated inflammatory cargo.
For example, two people with the same ApoB could have different underlying profiles. One might carry mostly LDL particles, while another has more triglyceride-rich remnants because of insulin resistance and impaired remnant clearance. A third may have a substantial contribution from genetically elevated Lp(a).
The particle count remains important in all three cases, but the surrounding biology may differ. Triglyceride-rich particles can carry remnant cholesterol and exchangeable apolipoproteins, while Lp(a) includes an additional apolipoprotein(a) structure capable of transporting oxidized phospholipids.
This complements rather than replaces earlier work showing why LDL particle characteristics can reveal risk that LDL-C misses. ApoB provides the broad particle count; more specific lipid and inflammatory markers help explain what makes up that count.
Key takeaway: ApoB estimates how many atherogenic particles are circulating, but it does not identify their type or biological behavior. The new research asks whether the composition of that ApoB burden helps explain differences in cardiovascular risk.
Three ApoB Particle Families
ApoB combines several lipoprotein classes into one particle count, but those particles differ in origin, composition and metabolism. The new study focused on three major groups: LDL, triglyceride-rich lipoproteins and Lp(a).
LDL particles are produced through the progressive metabolism of VLDL. The liver first releases triglyceride-rich VLDL particles to transport energy to peripheral tissues. As triglycerides are removed, these particles become smaller and may transition through IDL before becoming LDL.
LDL carries proportionally more cholesterol and less triglyceride than its VLDL precursor. Its principal atherogenic action begins when an LDL particle crosses the endothelium and becomes retained by molecules within the arterial wall. Prolonged exposure to a high number of circulating LDL particles increases the probability that this retention will occur.
Triglyceride-rich lipoproteins include liver-derived VLDL and intestinal chylomicrons, along with the remnant particles created as triglycerides are removed. The largest newly secreted particles are generally too large to enter the arterial wall efficiently, but their smaller remnants can penetrate and deliver substantial quantities of cholesterol.
This distinction is important because a triglyceride measurement does not directly count remnant particles. Triglycerides are cargo that can be removed, while the ApoB-containing particle remains in circulation until it is cleared. Remnants can therefore become progressively depleted of triglycerides and enriched in cholesterol.
Insulin resistance commonly increases hepatic VLDL production and interferes with normal triglyceride-rich particle metabolism. This can produce elevated triglycerides, remnant cholesterol, small dense LDL and a higher ApoB concentration—even when calculated LDL-C does not appear severely elevated.
Lp(a) is structurally different. It begins with an LDL-like particle containing ApoB-100, but an additional protein called apolipoprotein(a) is attached to it. The concentration is determined primarily by genetics and varies considerably among individuals.
Apolipoprotein(a) gives Lp(a) biological properties not shared by ordinary LDL. Lp(a) is an important carrier of oxidized phospholipids and has been connected with vascular inflammation, atherosclerotic cardiovascular disease and calcific aortic-valve disease. Its structure may also influence processes involving clot breakdown, although its clinical risk cannot be reduced to a single mechanism.
These differences explain why the same ApoB concentration can represent different lipoprotein profiles. ApoB counts the vehicles, but it does not describe whether those vehicles are predominantly LDL, metabolically driven remnants or genetically elevated Lp(a).
The new proteomic study investigated whether these structural and metabolic differences correspond to distinct biological responses. Its results suggest that triglyceride-rich particles and Lp(a) are associated with much broader inflammatory and vascular-remodeling signatures than LDL.
Key takeaway: LDL, triglyceride-rich remnants and Lp(a) all carry ApoB and can contribute to atherosclerosis, but they have different origins, cargo and associated biology. ApoB counts them together; additional testing helps identify what makes up the total burden.
What the Study Found
The researchers analyzed 2,918 circulating proteins in 35,269 UK Biobank participants who did not have coronary artery disease, peripheral artery disease or stroke at baseline. During follow-up, 1,599 participants developed coronary artery disease.
The investigators first identified proteins associated with the concentrations of LDL, triglyceride-rich lipoproteins and Lp(a). They adjusted for potential confounding factors and then used one-sample Mendelian randomization to look for associations supported by genetic variants that influence each lipoprotein exposure.
To qualify for the final signatures, a protein had to meet strict statistical criteria in both the observational and genetic analyses. This produced three very different proteomic profiles:
30 proteins associated with LDL
471 proteins associated with triglyceride-rich lipoproteins
53 proteins associated with Lp(a)
The number of associations does not automatically measure how dangerous each lipoprotein is. It indicates that triglyceride-rich particles were connected with a much broader pattern of circulating protein changes than LDL within this particular analytical framework.
The LDL signature was largely distinct from the other two groups. In contrast, the triglyceride-rich lipoprotein and Lp(a) signatures shared 36 proteins and showed common enrichment in pathways related to immune activation, inflammation and vascular remodeling.
The researchers then combined the associated proteins into multi-protein scores. After accounting for measured lipoprotein concentrations and other potential confounders, the triglyceride-rich lipoprotein score was associated with a 16% higher rate of incident coronary disease per standard-deviation increase. The Lp(a) score was associated with a 9% higher rate.
The LDL-associated protein score was not independently associated with coronary events after these adjustments. This does not mean LDL particles were harmless. The analysis evaluated whether the protein signature associated with LDL added information beyond the measured LDL exposure—not whether LDL itself caused coronary disease.
High-dimensional mediation analysis estimated that the proteomic alterations could explain approximately 62% of the coronary risk associated with triglyceride-rich lipoproteins and about 14% of the risk associated with Lp(a). The authors then replicated the main findings in 5,915 participants from the Multi-Ethnic Study of Atherosclerosis.
Replication and agreement with Mendelian-randomization analyses make the findings more persuasive than a simple cross-sectional protein screen. However, mediation estimates remain statistical models. They depend on assumptions about confounding, direction and relationships among the measured variables.
The published study therefore supports a biological distinction among ApoB-containing particles, but it does not provide a clinical formula for assigning an exact danger score to an individual LDL, remnant or Lp(a) particle.
Key takeaway: Triglyceride-rich lipoproteins and Lp(a) were associated with broader inflammatory and vascular-remodeling protein signatures than LDL. The findings suggest biological differences among ApoB particles without disputing the causal importance of overall ApoB exposure.
Particle Number and Particle Biology
ApoB and particle biology answer different questions. ApoB estimates how many atherogenic particles are circulating. Particle type helps explain what those particles carry, how they are cleared and which biological pathways may accompany their presence.
The number still matters because a particle must first circulate, cross the endothelium and become retained within the arterial wall before it can contribute directly to plaque. Higher ApoB creates more opportunities for that sequence to occur, particularly when exposure remains elevated for many years.
Once retained, however, particles may not produce identical consequences. An LDL particle is relatively cholesterol-rich compared with its size, but a triglyceride-rich remnant can carry considerably more cholesterol per particle. If that remnant enters the arterial wall, it may deliver a larger cholesterol payload in a single event.
Triglyceride-rich particles also carry exchangeable proteins such as ApoC-III and ApoE that influence lipolysis, clearance and interactions with vascular and immune cells. During triglyceride breakdown, lipolytic products—including fatty acids and other lipid components—may affect endothelial function and local inflammation.
Lp(a) adds another layer. Its LDL-like component can deposit cholesterol, while apolipoprotein(a) transports oxidized phospholipids and interacts with inflammatory and vascular pathways. Lp(a) is therefore not simply another LDL particle with a different name.
The new proteomic findings fit this model. The triglyceride-rich lipoprotein and Lp(a) signatures were strongly connected with immune activation and vascular remodeling, suggesting effects that extend beyond the physical delivery of cholesterol into the artery wall.
LDL’s smaller proteomic signature should not be interpreted as evidence that LDL is biologically inactive. LDL may exert much of its harm through cumulative arterial entry, retention and modification without producing the same broad pattern of circulating proteins. Plasma proteomics may also detect some biological pathways more effectively than others.
Particle properties can change after secretion. LDL may become oxidized, glycated or otherwise modified within a metabolically unhealthy environment. These changes can affect how the particle interacts with the endothelium and immune system, but they are not measured by a standard ApoB result.
This creates a useful framework:
ApoB describes exposure opportunity. Particle type and modification describe biological context.
Neither perspective makes the other unnecessary. A low inflammatory marker does not erase the risk created by prolonged exposure to a high ApoB concentration. Likewise, an acceptable ApoB result does not completely characterize risk from markedly elevated Lp(a), remnant particles or established plaque.
Key takeaway: ApoB particle number determines how many opportunities exist for arterial retention. Particle composition, cholesterol cargo, associated proteins and oxidative modification may influence what happens after those particles interact with the vessel wall.
Why Insulin Resistance Changes the ApoB Profile
Insulin resistance can change cardiovascular risk before LDL-C becomes dramatically elevated. One of its earliest lipid effects is increased production and delayed clearance of triglyceride-rich lipoproteins.
Adipose tissue normally responds to insulin by suppressing lipolysis. As adipose tissue becomes insulin resistant, more fatty acids are released into circulation and delivered to the liver. The liver can repackage this incoming energy into triglycerides and export it through ApoB-containing VLDL particles.
The insulin-resistant liver may also continue producing fat through de novo lipogenesis, even while insulin becomes less effective at suppressing hepatic glucose production. This selective insulin resistance helps produce the seemingly contradictory combination of elevated glucose output, hyperinsulinemia and continued triglyceride production.
As VLDL circulates, lipoprotein lipase removes part of its triglyceride cargo. The particles become progressively smaller, creating VLDL remnants, IDL and eventually LDL. When production is high or clearance is impaired, more remnant particles remain in circulation.
These remnants matter because they can enter the arterial wall and carry substantial quantities of cholesterol. A routine lipid panel may show their presence indirectly through elevated triglycerides and calculated remnant cholesterol, but it does not count them directly.
Cholesteryl ester transfer protein also exchanges triglycerides from VLDL with cholesterol carried by LDL and HDL. Subsequent processing can produce triglyceride-enriched LDL that becomes smaller and denser, while HDL particles may be cleared more rapidly. The resulting pattern often includes:
Elevated triglycerides
Low HDL-C
Increased remnant particles
Small dense LDL
ApoB that is higher than LDL-C alone would suggest
This is why LDL-C can underestimate particle burden in people with type 2 diabetes, metabolic syndrome, fatty liver or abdominal obesity. The cholesterol inside each LDL particle may be relatively low while the total number of ApoB-containing particles remains high.
ApoC-III may further contribute by slowing the clearance of triglyceride-rich particles and interfering with normal triglyceride metabolism. It also appeared among the biological pathways of interest in research examining the inflammatory effects of triglyceride-rich lipoproteins.
The unusually broad proteomic signature identified in the new study may therefore reflect more than triglyceride cargo. It may capture the combined effects of remnant accumulation, altered apolipoproteins, lipolysis products, insulin resistance and vascular inflammation.
As discussed in Quick Lab Mobile’s guide to high triglycerides and insulin resistance, triglycerides should not be interpreted as an isolated dietary number. They can signal a larger change in hepatic energy handling and ApoB-particle metabolism.
Key takeaway: Insulin resistance can shift the ApoB burden toward VLDL and remnant particles, producing cardiovascular risk that LDL-C alone may underestimate. Triglycerides, HDL-C, remnant cholesterol and ApoB help reveal this pattern.
Why Lp(a) Is More Than Another LDL Particle
Lp(a) contains an LDL-like particle with one ApoB-100 molecule, so it contributes to the total ApoB measurement. However, its additional apolipoprotein(a) structure gives it biological properties that ordinary LDL does not share.
Apolipoprotein(a) is attached to ApoB by a disulfide bond and varies considerably in size among individuals. The number of repeated kringle structures within apolipoprotein(a) influences how much Lp(a) the liver produces. Smaller isoforms are often associated with higher circulating concentrations.
This production is determined primarily by variation in the LPA gene. Diet, exercise and weight loss can improve many cardiovascular markers but usually have relatively modest effects on genetically elevated Lp(a). Someone can therefore have excellent metabolic health and still carry substantial inherited Lp(a)-related risk.
Lp(a) can contribute to atherosclerosis through its LDL-like core, which transports cholesterol into the arterial wall. However, it is also a major carrier of oxidized phospholipids. These modified lipids can activate endothelial and immune pathways associated with inflammation, plaque progression and calcification.
This may help explain why Lp(a) is associated not only with coronary artery disease but also with calcific aortic-valve disease. ApoB counts the Lp(a) particle, but it does not reveal the oxidized phospholipid burden attached to that particle.
The new proteomic study identified 53 proteins associated with Lp(a). Thirty-six overlapped with the triglyceride-rich lipoprotein signature, with shared enrichment in inflammatory and vascular-remodeling pathways. This overlap suggests that structurally different particles may converge on some of the same downstream biological processes.
However, the estimated mediation was much smaller for Lp(a) than for triglyceride-rich particles. Proteomic changes statistically explained approximately 14% of Lp(a)-associated coronary risk, leaving most of the association unexplained by the measured proteins.
That remaining risk may involve arterial cholesterol deposition, oxidized phospholipids, local processes not well represented in circulating plasma proteins or biological pathways not included in the proteomic panel. The mediation result should not be interpreted to mean that only 14% of Lp(a) matters.
ApoB alone also cannot identify whether Lp(a) is elevated. Two people can have the same ApoB concentration while one has very little Lp(a) and the other has a substantial genetically determined concentration. Direct Lp(a) measurement is required to distinguish them.
This expands on the distinction discussed in Quick Lab Mobile’s article about cholesterol and atherosclerosis: particle burden is important, but oxidation, inflammation and particle composition help determine the biological context in which that burden operates.
Key takeaway: Lp(a) contributes one particle to the ApoB count, but its apolipoprotein(a) structure and oxidized phospholipid cargo add information that ApoB cannot provide. Measuring ApoB does not eliminate the need to measure Lp(a) directly.
What to Measure Alongside ApoB
ApoB should remain central because it estimates the total number of atherogenic particles. The new research does not provide a reason to replace it with an inflammatory marker or a large proteomic panel. It instead shows why ApoB is more informative when interpreted with tests that identify particle type and metabolic context.
A conventional lipid panel provides the starting structure. LDL-C estimates cholesterol carried within LDL, while triglycerides reflect the circulating triglyceride burden carried mainly by VLDL and other triglyceride-rich particles. HDL-C adds metabolic context but does not directly measure HDL function.
Non-HDL cholesterol is calculated by subtracting HDL-C from total cholesterol. It captures cholesterol contained in all ApoB particles—including LDL, remnants and Lp(a)—making it useful when triglycerides are elevated or LDL-C may not represent the complete atherogenic burden.
Remnant cholesterol can be estimated by subtracting LDL-C and HDL-C from total cholesterol. It approximates cholesterol carried by triglyceride-rich remnants, but it remains a calculated value and does not directly count remnant particles. Its accuracy also depends on the accuracy of the LDL-C calculation.
ApoB helps determine whether the cholesterol values are being transported in relatively few or many particles. When ApoB is higher than LDL-C would suggest, insulin resistance, triglyceride-rich remnants and smaller cholesterol-depleted LDL particles should be considered. QLM’s article on small dense LDL explains this discordance in greater detail.
Lp(a) must be measured directly because neither ApoB nor LDL-C can determine how much is present. Results may be reported in milligrams per deciliter or nanomoles per liter, and these units should not be converted using one universal factor because particle mass varies with apolipoprotein(a) isoform size.
LDL particle number and ion-mobility testing can provide additional information about LDL concentration, size and distribution. These tests may be particularly useful when ApoB, LDL-C, triglycerides and the clinical risk profile disagree. They refine the profile but do not make total ApoB exposure irrelevant.
Inflammatory markers answer a different question. hs-CRP measures systemic inflammatory signaling and may help identify residual inflammatory risk, but it does not determine which lipoprotein caused that inflammation. Infection, injury, autoimmune disease and other temporary conditions can also elevate it.
Oxidized LDL and Lp-PLA2 may provide additional information in selected assessments, although their standardization and clinical roles are less established than ApoB, Lp(a), conventional lipids and hs-CRP. More testing is not automatically better unless the result can meaningfully change risk interpretation or management.
Fasting glucose, fasting insulin, HbA1c and the triglyceride-to-HDL ratio help reveal the metabolic environment producing the lipoprotein pattern. This is particularly important when triglyceride-rich particles appear to be a large component of the ApoB burden. QLM’s guide to high triglycerides and insulin resistance explains how hepatic VLDL production connects these findings.
Finally, laboratory markers estimate risk factors rather than measure plaque directly. Coronary artery calcium scoring or other cardiovascular imaging may provide additional information when the treatment decision remains uncertain after considering age, symptoms, family history and laboratory findings.
Key takeaway: ApoB measures total atherogenic particle burden. Triglycerides, non-HDL cholesterol, remnant cholesterol, Lp(a), particle analysis, inflammation markers and metabolic testing help explain what makes up that burden and the environment in which those particles are circulating.
What This Research Changes—and What It Does Not
This research adds biological detail to the ApoB model without overturning it. ApoB remains the most practical way to estimate the total number of atherogenic particles circulating in the blood. Every LDL particle, triglyceride-rich remnant and Lp(a) particle carries one ApoB molecule, which is why ApoB provides a more direct particle count than LDL cholesterol alone.
What the new findings suggest is that equal numbers of different ApoB-containing particles may not create risk through identical pathways. LDL appeared to have a relatively narrow proteomic signature, while triglyceride-rich lipoproteins were associated with hundreds of proteins involved in immune activity, inflammation and vascular remodeling. Lp(a) showed a smaller but similarly distinctive biological signature.
This distinction may help explain why two people with the same ApoB concentration can have different cardiovascular risk profiles. One person may carry predominantly cholesterol-rich LDL particles, while another has more triglyceride-rich remnants associated with insulin resistance, fatty liver and post-meal lipemia. A third may have genetically elevated Lp(a), adding oxidized phospholipids, inflammation and possible thrombotic effects to the risk created by particle entry into the arterial wall.
The study also estimated that the measured proteomic changes statistically mediated approximately 62% of the coronary risk associated with triglyceride-rich lipoproteins, compared with about 14% of the risk associated with Lp(a). These results suggest that downstream biological responses may contribute substantially to risk, particularly for remnant particles. However, statistical mediation does not prove that each associated protein directly causes atherosclerosis or that measuring these proteins will improve patient care. The European Heart Journal study
The practical conclusion is not that ApoB has become less useful. It is that ApoB answers one important question—how many atherogenic particles are present—while triglycerides, remnant cholesterol, Lp(a), inflammatory markers and metabolic health help explain what kinds of particles are present and what biological environment they are entering.
Cardiovascular assessment should therefore avoid choosing between particle number and particle biology. The most complete picture comes from considering both.
Key takeaway: ApoB remains the central measure of atherogenic particle burden, but it does not capture every biological difference among LDL, triglyceride-rich remnants and Lp(a). Particle number establishes the opportunity for arterial exposure; particle type and the surrounding metabolic environment may influence how that exposure becomes disease.
Conclusion
ApoB remains one of the most useful measurements for understanding cardiovascular risk because it estimates how many atherogenic particles are circulating in the blood. The greater the particle burden, the more opportunities those particles have to enter the arterial wall and contribute to plaque formation.
The emerging research does not challenge that principle. Instead, it shows that particle count is only one layer of the story. LDL, triglyceride-rich remnants and Lp(a) all carry ApoB, but they differ in composition, metabolism and the biological pathways they may activate.
Triglyceride-rich particles appear closely connected with immune activation, vascular remodeling and the metabolic disturbances associated with insulin resistance. Lp(a) adds genetically influenced risk through its ApoB-containing structure, oxidized phospholipids and additional inflammatory and thrombotic properties. LDL remains atherogenic, but its proteomic signature appears different from those of remnants and Lp(a).
This means that cardiovascular assessment should not depend on LDL cholesterol alone—or even ApoB alone. ApoB establishes the overall burden of atherogenic particles, while triglycerides, remnant cholesterol, Lp(a), glucose regulation, fasting insulin and inflammatory markers provide additional context. When appropriate, coronary calcium scoring and other imaging can help determine whether these biological risks have already translated into detectable disease.
The central lesson is not that some ApoB particles are harmless. It is that the same ApoB concentration can represent different combinations of particles operating in different metabolic environments. Understanding those differences can produce a more complete and individualized assessment than a standard cholesterol panel by itself.
QuickLab Mobile offers convenient at-home blood collection in Miami for ApoB, Lp(a), advanced lipid testing, fasting insulin, glucose regulation and inflammatory markers. Results should be interpreted together with medical history, medications, imaging and overall cardiovascular risk.
👉 Need a specimen collection?. Book Now
Disclaimer:
The information provided in this blog, podcast, and associated content is for educational and informational purposes only and is not intended as a substitute for professional medical advice, diagnosis, or treatment. The content shared is based on reputable sources, medical literature, and expert insights, but it should not be used as a replacement for direct consultation with a licensed healthcare provider.
No Doctor-Patient Relationship: Engaging with this content does not create a doctor-patient relationship between you and QuickLabMobile or any contributors. Always consult with a qualified physician, specialist, or healthcare professional before making any medical decisions, changing your treatment plan, or starting/stopping any medications.
Not a Substitute for Medical Advice: While we strive to provide accurate and up-to-date information, medicine is constantly evolving. New research, treatments, and medical recommendations may emerge, and individual health conditions can vary. Do not rely solely on this content for health decisions. If you are experiencing symptoms, have concerns about your health, or require medical assistance, seek immediate care from a licensed medical professional.
Emergency Situations: If you are experiencing a medical emergency, such as difficulty breathing, chest pain, signs of a stroke, or any other life-threatening condition, call 911 (or your local emergency services) immediately. Do not delay seeking emergency care based on information provided here.
Liability Disclaimer: QuickLabMobile, its contributors, and any associated entities do not assume liability for any damages, harm, or adverse outcomes resulting from the use, interpretation, or misuse of the information provided in this content. You are responsible for your own healthcare decisions and should always verify information with a trusted medical professional.
External Links & References: This content may include links to external sources, medical studies, or third-party websites for further reading. These links are provided for convenience and informational purposes only. QuickLabMobile does not endorse, control, or take responsibility for the accuracy of external content. Always verify information with authoritative sources such as the CDC, NIH, WHO.
Final Note: Your health is unique, and what works for one person may not be suitable for another. Stay informed, ask questions, and always prioritize professional medical guidance


